
Getting a diagnosis of lung cancer can be overwhelming. But knowing what to expect can help you feel more prepared.
How is lung cancer diagnosed and tested?

There’s no single test for lung cancer. Most people will have several checks to help doctors understand what’s going on, from scans and blood tests to looking at tissue under a microscope. These tests are used to find out if it is lung cancer, what type it is, and whether it’s spread.
If it is cancer, some tests also look for changes in the cancer’s DNA (called biomarkers) to help decide which treatment is most likely to work.
The route to a lung cancer diagnosis
There is no single test for lung cancer. Most people go through a series of checks, scans and tests, and the order can vary from person to person and country to country. Select each step to see what usually happens.
First checks
Your doctor will ask about your symptoms and how long you have had them, your general health, any medicines you take, lung cancer in your close family, and whether you have ever smoked or been exposed to things like asbestos or radon.
They will usually listen to your chest and may arrange blood tests. In many countries the first scan is a chest X-ray. If anything suggests lung cancer, you should be referred quickly to a lung specialist, often at a hospital.
Tests you might have
- Questions and examination
- Blood tests
- Chest X-ray
Who you might see
- Family doctor or GP
- Respiratory specialist
Scans
A CT scan of the chest and upper abdomen is usually the main scan. It shows the size and position of anything unusual, and whether lymph nodes in the chest look enlarged.
Depending on the CT results, you may then have a PET-CT scan to look for any spread and help plan treatment, and sometimes a scan of the brain. Scans can strongly suggest lung cancer, but they cannot confirm it on their own.
Tests you might have
- CT scan
- PET-CT scan
- Brain MRI or CT
- Ultrasound
Who you might see
- Radiographer
- Radiologist
Taking a sample
The only way to be certain it is lung cancer is to look at cells under a microscope. The team will choose the safest and simplest way to reach the area, which depends on where it is in the body.
Often one procedure can take samples from the lung and the lymph nodes at the same time, which helps with both diagnosis and staging. Occasionally a sample is too risky to take, and the team may recommend going straight to surgery if the scans strongly suggest cancer.
Tests you might have
- Bronchoscopy
- EBUS
- CT-guided biopsy
- Pleural aspiration
- Neck lymph node biopsy
Who you might see
- Respiratory specialist
- Radiologist
- Thoracic surgeon
In the laboratory
A pathologist examines the sample to find out whether it is cancer and, if so, which type. This is important because different types of lung cancer are treated in different ways.
For non-small cell lung cancer, the sample is also tested for biomarkers, such as gene changes and the PD-L1 protein. Biomarker results can take longer than the first results, sometimes a couple of weeks, and are needed before some treatments can start.
Tests you might have
- Pathology
- Biomarker testing
- PD-L1 test
- Liquid biopsy
Who you might see
- Pathologist
- Laboratory scientists
Team review and results
A team of specialists, often called a multidisciplinary team or MDT, looks at all of your scans and test results together. They agree the type and stage of the cancer and the treatment options that could suit you.
Your results should be explained to you in person, with time for questions. Some people also have lung function and fitness tests at this point, to check which treatments are safe for them.
Tests you might have
- Lung function tests
- Heart and fitness tests
Who you might see
- Respiratory specialist
- Lung cancer nurse
- Oncologist
- Thoracic surgeon
Waiting for tests and results can be one of the hardest parts. If your symptoms get worse while you wait, contact your care team or doctor.
Lung cancer tests explained
Not everyone needs every test. Your team will choose the ones that make sense for you. Filter by type of test, then open any test to read what it is, what it can show and what to expect on the day.
Showing all 18 tests
Chest X-rayA quick picture of the chest
Scans
What it is
A picture of the inside of your chest, taken using a small amount of radiation.
What it can show
Shadows, fluid or a collapsed area of lung. A chest X-ray can miss some lung cancers, so a normal result does not always rule it out. If your symptoms carry on, go back to your doctor.
What to expect
It takes a few minutes. You stand against the machine and hold your breath for a moment.
CT scanThe main scan for lung cancer
Scans
What it is
A series of X-rays put together by a computer to build a detailed picture of the inside of your body.
What it can show
The size and position of anything unusual in the lung, whether lymph nodes in the chest look enlarged, and the liver and adrenal glands.
What to expect
You lie on a bed that moves through a ring-shaped scanner. It usually takes 10 to 15 minutes. You may have an injection of contrast dye, which can make you feel warm for a moment.
PET-CT scanShows how active cells are
Scans
What it is
A CT scan combined with a PET scan. A small amount of a radioactive sugar, called a tracer, is injected and collects in areas where cells are very active, such as cancer cells.
What it can show
Whether cancer may have spread to lymph nodes or other parts of the body. It helps the team work out the stage and plan treatment.
What to expect
You may be asked not to eat for a few hours before. After the injection you rest for about an hour, then the scan takes around 30 minutes. You will be told about any precautions afterwards.
Brain MRI or CT scanChecks whether cancer has reached the brain
Scans
What it is
An MRI uses magnets and radio waves to build detailed pictures. Some people have a CT scan of the head instead.
What it can show
Whether lung cancer has spread to the brain. It is usually offered when treatment aims to cure the cancer, or if you have symptoms such as headaches.
What to expect
For an MRI you lie inside a tube-shaped scanner, which is noisy, for 30 to 45 minutes. Tell the team if you have a pacemaker or any metal in your body.
Ultrasound scanUses sound waves
Scans
What it is
Sound waves create a picture on a screen. It is painless and uses no radiation.
What it can show
Fluid around the lung, lymph nodes in the neck, or the liver. It is often used to guide a needle when taking a sample or draining fluid.
What to expect
Gel is put on your skin and a small probe is moved over the area. It usually takes 10 to 20 minutes.
BronchoscopyA look inside the airways
Taking a sample
What it is
A thin, flexible tube with a camera, called a bronchoscope, is passed through your nose or mouth into the airways.
What it can show
The doctor can see inside the airways and take small samples of tissue, cells or fluid to check for cancer.
What to expect
You will usually have a sedative to help you relax and a spray to numb your throat. It takes around 20 to 30 minutes. You will need someone to take you home if you have sedation.
EBUSSamples lymph nodes without surgery
Taking a sample
What it is
Endobronchial ultrasound. A bronchoscope with a small ultrasound probe on the end lets the doctor see through the airway walls.
What it can show
A fine needle takes samples from lymph nodes in the centre of the chest. This can confirm the diagnosis and show whether the cancer has spread to the lymph nodes, at the same time.
What to expect
Similar to a bronchoscopy, with sedation or a general anaesthetic. It usually takes 30 to 60 minutes. A similar test, called EUS, is done through the food pipe.
CT-guided lung biopsyA needle sample through the chest wall
Taking a sample
What it is
A thin needle is passed through the skin of your chest into the lung, using a CT scan to guide it to the right place.
What it can show
Cells or tissue from an area in the outer part of the lung, which a bronchoscope may not be able to reach.
What to expect
Your skin is numbed with local anaesthetic and you will be asked to lie still and hold your breath at times. You stay for a few hours afterwards so the team can check for air leaking around the lung, which is an uncommon side effect.
Pleural aspirationDraining fluid from around the lung
Taking a sample
What it is
Fluid can build up between the lung and the chest wall, called a pleural effusion. A needle is used to drain some of it, usually guided by ultrasound.
What it can show
Cancer cells in the fluid. Draining the fluid can also ease breathlessness.
What to expect
Your skin is numbed with local anaesthetic and you sit leaning forward. It usually takes 15 to 30 minutes.
ThoracoscopyA camera inside the chest
Taking a sample
What it is
A camera is passed through a small cut in the side of your chest to look at the lining of the lung, called the pleura.
What it can show
The team can take samples from the pleura and drain fluid at the same time.
What to expect
This may be done with local anaesthetic and sedation, or under general anaesthetic by a surgeon. You may need to stay in hospital for a night or more.
Neck lymph node biopsyA quick sample from the neck
Taking a sample
What it is
If a lymph node in your neck is enlarged, a fine needle can take a sample, usually guided by ultrasound.
What it can show
Whether cancer cells are in the lymph node. This can sometimes give a diagnosis and stage with one simple test.
What to expect
Your skin is numbed with local anaesthetic. It takes around 15 to 30 minutes.
MediastinoscopySurgery to sample lymph nodes
Taking a sample
What it is
A surgeon makes a small cut at the base of the neck and passes a tube into the centre of the chest, under general anaesthetic.
What it can show
Samples from lymph nodes in the centre of the chest. It is used less often now that EBUS is widely available.
What to expect
You are asleep for the procedure and may stay in hospital overnight.
Blood testsA picture of your general health
Laboratory tests
What it is
Samples of blood are checked in a laboratory.
What it can show
Your blood counts and how well your liver, kidneys and bones are working. Blood tests cannot diagnose lung cancer on their own, but help the team plan safe treatment.
What to expect
A few minutes. Some tests need you to avoid eating beforehand, and the team will tell you if so.
Biomarker testingLooks for changes in the cancer
Laboratory tests
What it is
Laboratory tests on a tissue sample that look for changes in the cancer's genes, such as EGFR, ALK, ROS1, KRAS, BRAF, MET, RET, HER2 and NTRK. Many laboratories test for all of them at once using next-generation sequencing, or NGS.
What it can show
Whether the cancer has a change that a targeted treatment can work against. Biomarker testing is recommended for people with advanced non-small cell lung cancer, and some biomarkers are also tested in earlier stages.
What to expect
It uses the sample already taken, so there is usually nothing extra for you to do. Results can take a couple of weeks. Ask your team whether your cancer has been tested and what the results showed.
Liquid biopsyA blood test for cancer DNA
Laboratory tests
What it is
A blood test that looks for small pieces of DNA released by cancer cells into the bloodstream, called circulating tumour DNA.
What it can show
Some of the same gene changes as tissue biomarker testing. It can be quicker, or useful when there is not enough tissue.
What to expect
A normal blood test. If no change is found, you may still need a tissue test, because some cancers release very little DNA into the blood.
PD-L1 testHelps decide on immunotherapy
Laboratory tests
What it is
A test on the tissue sample that measures how many cancer cells have a protein called PD-L1 on their surface. The result is given as a percentage.
What it can show
How likely the cancer is to respond to some immunotherapy treatments. A high result usually means immunotherapy is more likely to help.
What to expect
It uses the sample already taken, so there is nothing extra for you to do.
Lung function testsHow well your lungs work
Fitness for treatment
What it is
Breathing tests where you blow into a machine, sometimes called spirometry and gas transfer.
What it can show
How much air your lungs hold and how well they move oxygen into your blood. This helps the team decide whether surgery or radiotherapy is safe for you.
What to expect
You breathe in and out as hard and fast as you can, a few times. It takes 20 to 45 minutes.
Heart and fitness testsChecks you are fit for treatment
Fitness for treatment
What it is
Tests such as an ECG or a heart ultrasound, called an echocardiogram, and exercise tests such as a walking or stair-climbing test or an exercise bike test.
What it can show
How well your heart and body cope with effort, which helps the team plan treatment that is safe for you.
What to expect
These vary. Wear comfortable clothes and shoes for exercise tests.
Tests, waiting times and how results are shared vary between countries and hospitals. If you are unsure why you are having a test, ask your team to explain.
What your results tell you
Once all the results are in, the team can describe the cancer in three ways: its type, its stage and its biomarkers. Together these guide which treatments are likely to work best. Type and stage are explained here, and biomarkers further down this page.
Which type of lung cancer is it?
The type depends on the kind of cell the cancer started in, seen under a microscope. There are two main groups, and they are treated differently.
Adenocarcinoma
The most common type, around 4 to 5 in 10
Starts in cells that make mucus, often in the outer parts of the lung. It is the most common type in people who have never smoked, and the type most likely to have a targetable biomarker.
Squamous cell carcinoma
Around 1 in 4
Starts in the flat cells lining the airways, often near the centre of the chest. It is more common in people who have smoked.
Other non-small cell types
Less common
Includes large cell carcinoma and rarer types. Sometimes the cells cannot be classified further, and this may be called non-small cell lung cancer not otherwise specified.
Small cell lung cancer
Around 15 in 100
Tends to grow and spread more quickly, so treatment usually starts very soon after diagnosis. It is more common in people who have smoked, but people who have never smoked can get it too.
Figures are approximate and vary between countries. Some less common tumours in the lung, such as carcinoid tumours, are treated differently. Mesothelioma starts in the lining of the lung and is a different cancer.
How far has it spread?
The stage describes the size of the cancer and whether it has spread. Select a stage to see what it means.
Stage 1
The cancer is small and has not spread outside the lung or to any lymph nodes.
- TTumour: the size of the main tumour and whether it has grown into nearby areas
- NNodes: whether cancer has spread to lymph nodes, and how far
- MMetastasis: whether cancer has spread to other parts of the body
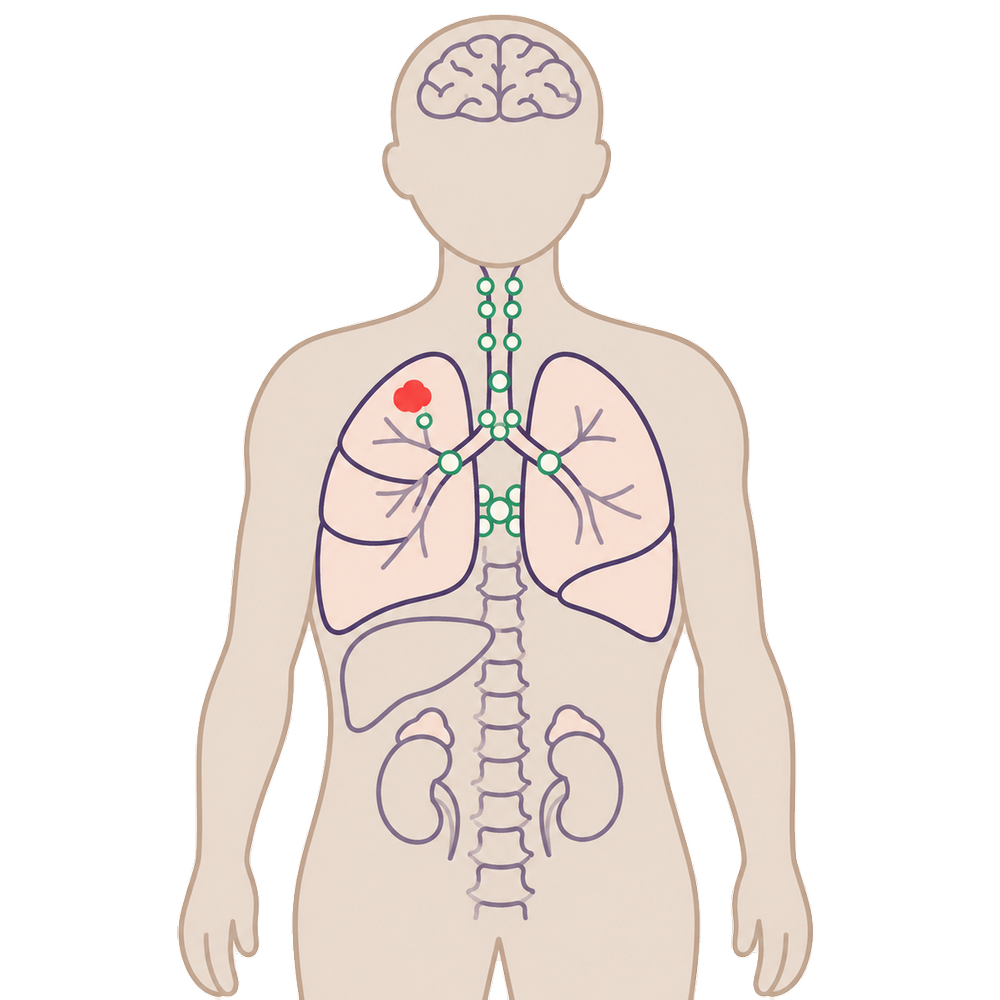

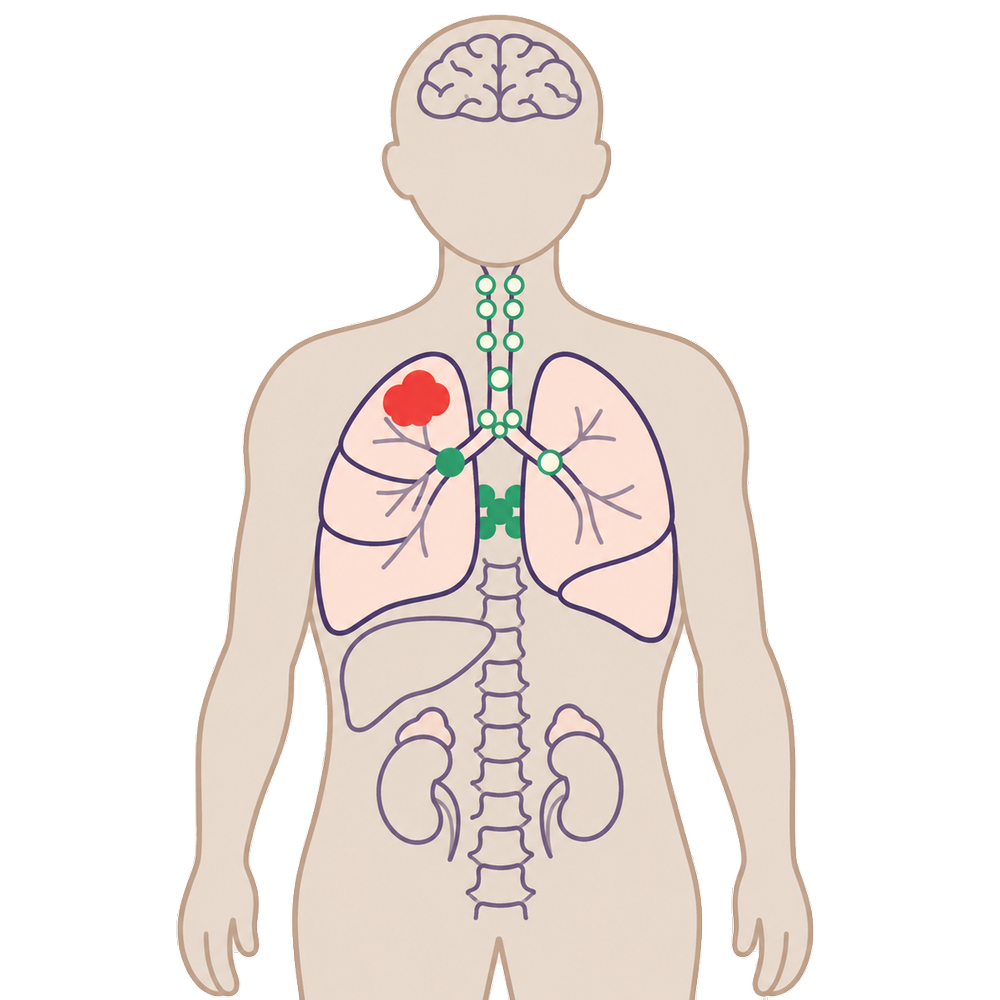
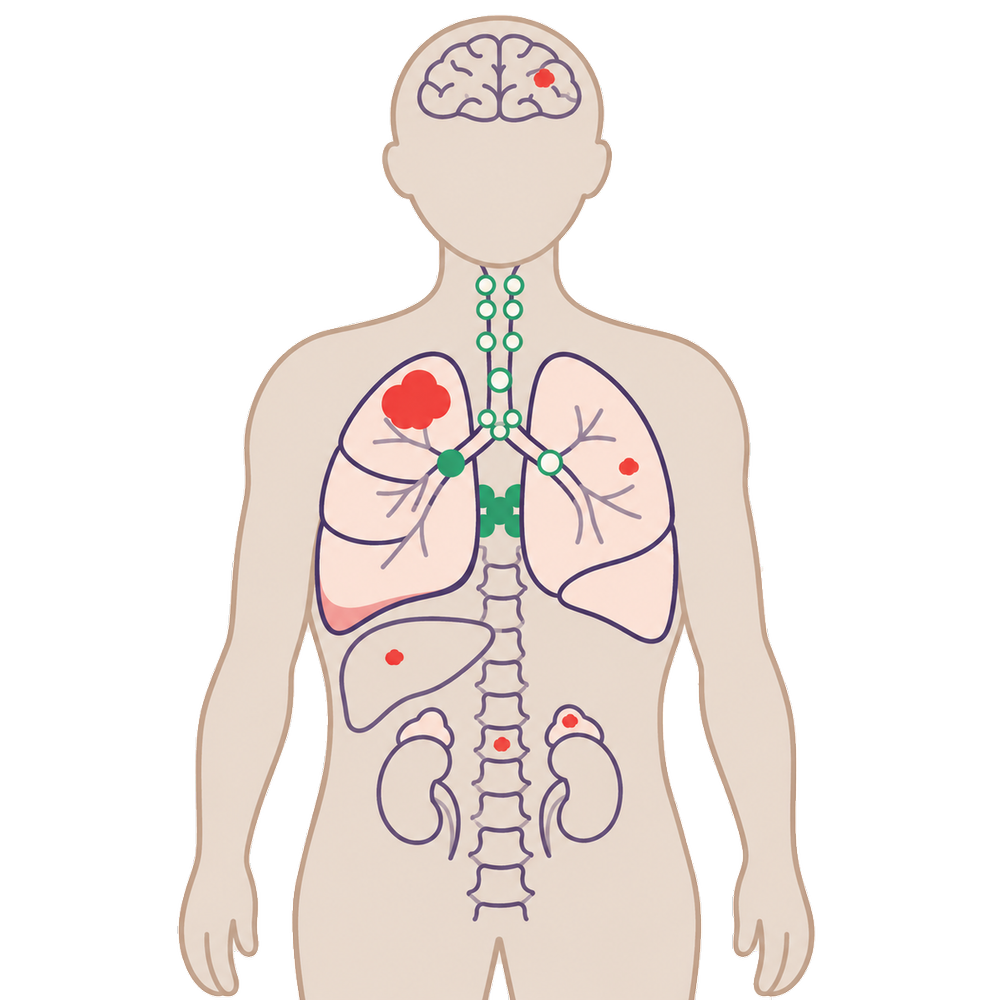
This is a simplified guide. Each stage is split further, for example 1A or 3B, using the TNM system. Small cell lung cancer is often also described as limited or extensive. Ask your team to explain what your stage means for you.
What are biomarkers?
Biomarkers are changes in your cancer cells that can be tested for in a biopsy sample. These changes can affect how the cancer behaves, and what treatment might work best.
Some biomarkers are found in the genes of the tumour (like EGFR, ALK or KRAS). Others are proteins found on the surface of cells (like PD-L1).
Your care team may test for biomarkers using tissue or blood samples.
Why is biomarker testing important?
Testing for biomarkers can help:
Match you with a treatment that targets your specific type of cancer.
Avoid treatments that are less likely to work.
Improve your chances of a better outcome.
There are over 20 known lung cancer biomarkers. Some are linked to targeted therapies or immunotherapy. Not everyone will have a biomarker that affects treatment, but testing gives the information needed to make the best plan.
Lung cancer biomarkers at a glance
Select a biomarker to find out what it is and roughly how often it is found. The dots show about how many people in every 100 with non-squamous non-small cell lung cancer have it.
Gene change
EGFR
Figures are approximate, based on European studies, and vary between countries and groups of people. Targeted treatments are approved in Europe for at least some changes in each of the genes shown, but what is available differs from country to country. Sources: ESMO Clinical Practice Guidelines for non-small cell lung cancer.
Words you might hear
Medical teams use a lot of specialist words. Search for a word, or browse the list, to find out what it means.
35 words
- Adenocarcinoma
- The most common type of non-small cell lung cancer. It starts in cells that make mucus.
- Adrenal glands
- Two small glands above the kidneys. Lung cancer can sometimes spread there.
- Biomarker
- A gene change or protein in the cancer that can be tested for, and can help decide which treatment is most likely to work.
- Biopsy
- Taking a small sample of tissue or cells so it can be looked at under a microscope.
- Bronchoscopy
- A test using a thin, flexible tube with a camera to look inside the airways and take samples.
- Contrast
- A dye, usually injected into a vein, that makes some scans clearer.
- ctDNA
- Circulating tumour DNA. Small pieces of DNA from cancer cells found in the blood, tested in a liquid biopsy.
- Cytology
- Looking at individual cells, for example from fluid or a needle sample, under a microscope.
- EBUS
- Endobronchial ultrasound. A bronchoscopy with an ultrasound probe, used to take samples from lymph nodes in the chest.
- Fusion
- When two genes join together abnormally. ALK, ROS1, RET and NTRK changes are usually fusions.
- Histology
- Looking at tissue under a microscope to find out the type of cancer.
- Immunotherapy
- Treatment that helps your own immune system recognise and attack cancer cells.
- Lung cancer nurse
- A specialist nurse who supports people through tests and treatment, and is often the main contact.
- Lymph nodes
- Small, bean-shaped glands that are part of the immune system. Lung cancer can spread to the lymph nodes in the chest or neck.
- MDT
- Multidisciplinary team. The group of specialists who review your results together and agree a treatment plan.
- Mediastinum
- The area in the centre of the chest, between the lungs, which contains the heart, windpipe and many lymph nodes.
- Metastasis
- Cancer that has spread from where it started to another part of the body. Also called secondary cancer.
- Mutation
- A change in a gene. Some mutations in lung cancer can be treated with targeted medicines.
- NGS
- Next-generation sequencing. A laboratory test that checks many genes at once for changes.
- Nodule
- A small spot or shadow on a lung scan. Most nodules are not cancer, but some need checking or monitoring.
- NSCLC
- Non-small cell lung cancer, the most common group of lung cancers, which includes adenocarcinoma and squamous cell carcinoma.
- Oncologist
- A doctor who specialises in treating cancer with medicines or radiotherapy.
- Pathologist
- A doctor who examines tissue and cells in the laboratory to make a diagnosis.
- PD-L1
- A protein on cancer cells that can stop the immune system from attacking them. Testing for it helps decide on immunotherapy.
- PET-CT
- A scan that shows how active cells are in different parts of the body, used to check whether cancer has spread.
- Pleura
- The two thin layers of tissue that cover the lungs and line the inside of the chest.
- Pleural effusion
- A build-up of fluid between the layers of the pleura, which can cause breathlessness.
- Radiologist
- A doctor who specialises in reading scans and carrying out scan-guided procedures.
- Respiratory specialist
- A doctor who specialises in lung conditions, also called a pulmonologist or chest physician.
- SCLC
- Small cell lung cancer. A less common type that tends to grow quickly.
- Squamous cell carcinoma
- A type of non-small cell lung cancer that starts in the flat cells lining the airways.
- Staging
- Working out the size of the cancer and whether, and how far, it has spread.
- Targeted therapy
- Medicines that work against a specific change in cancer cells, such as an EGFR mutation.
- Thoracic surgeon
- A surgeon who operates on the lungs and chest.
- TNM
- The staging system for lung cancer, based on the tumour (T), lymph nodes (N) and spread to other parts of the body (M).
No words match your search. Try a shorter word, or ask your care team to explain.